Tag Archives: resuscitation

Is The Mechanical CPR Device The Next MAST Trousers? Part 2

In my last post, I provided information on the history of the mechanical CPR device. Today I’ll examine the results of a paper published just two weeks ago that studied the rates of favorable neurological survival and overall survival to discharge in patients treated with this device.

A small group of researchers from St. Luke’s Hospital in Kansas City, Emory University in Atlanta, and the University of Texas Southwestern in Dallas performed this study. It was a seven-year, observational cohort study that used the Cardiac Arrest Registry to  Enhance Survival database. This is a prospective, multicenter registry of patients with out-of-hospital cardiac arrest in the U.S. It has a large catchment area of 200 million residents, representing about 60% of the U.S. population.

To evaluate the impact of using a mechanical CPR device for these patients, the agencies evaluated had to have submitted two or more years of data before they started using it. The researchers then evaluated whether introducing the mechanical CPR device was associated with higher survival to discharge or favorable neurological survival.

Here are the factoids:

  • The control group consisted of nearly 52,000 patients, involving 73 EMS agencies. They did not adopt the use of the device during the study period. Simple trends over time were studied.
  • The study group was 49 agencies with 32,000 patients that did begin using the device.
  • Overall favorable neurologic survival ranged from 9.6% to 10.6%, and survival to discharge ranged from 11.1% to 12.0% in the control group. These were not significant differences. It suggests there was no long-term change in these rates due to other factors.
  • In the study group, favorable neurologic survival was 8.9% before mechanical CPR device use, and 8.3% after. This was not a significant difference.
  • Also in the study group, survival to discharge was 11.0% before and 10.0% after. This was not a significant difference.
  • There were no improved outcomes between agencies that used the devices heavily, or if 911-witnessed arrests were included.

The authors concluded that EMS agency rates of favorable neurologic survival and survival to discharge were not any higher at agencies that started using mechanical CPR devices.

Bottom line: This study shows no improvement in two kinds of survival among patients treated by EMS agencies that adopted the mechanical CPR device. It did not evaluate the quality of the CPR applied. However, this is implied in the reason for using this device and the marketing materials provided by the manufacturers. 

This paper provides strike one for using the mechanical CPR device to improve survival. In my next post, I’ll review several smaller randomized clinical trials looking at the impact of these devices. Then I’ll finish up with an analysis of a Cochrane Systematic Review on the benefit of this device. 

Reference: Mechanical CPR Device Use and Cardiac Arrest Survival in EMS Agencies. Circulation. 2026 Aug 11;154(6):532-541. doi: 10.1161/CIRCULATIONAHA.126.079272. Epub 2026 Jun 18. PMID: 42312381; PMCID: PMC13286238.

Is The Mechanical CPR Device The Next MAST Trousers? Part 1

It’s very common to see major trauma patients arriving in the trauma bay with a mechanical CPR device strapped to their chest, pounding away. How did this idea start? How effective are they? As you know, anything entrenched in our daily practice to the point that we don’t even question it is fair game for scrutiny in this blog.

I’ve seen these devices used in my trauma patients for about 20 years. They keep getting sleeker and smaller, so I wanted to look at the backstory of these tools.

Why do we even need something like this? Well, there are a few things that we are fairly certain of. First, the survival rate after an out-of-the-hospital cardiac arrest is dismal. Many well-accepted studies estimate survival at about 10%. Second, we also have good data that CPR improves survival in out-of-hospital cardiac arrest. If bystanders start CPR within one minute of arrest, survival to discharge from the hospital increases to 22%. Of course, it decreases as the time interval to start it increases.

We also know that CPR quality can vary based on provider training, fatigue, hand placement, compression depth, and other factors. I’m not aware of any papers that have quantified this. In contrast, mechanical CPR machines provide constant, high-quality compressions and do not get tired. These compressions can be continued indefinitely.

It would seem logical, then, that providing continuous, high-quality CPR is a good thing. But a few of us seasoned trauma professionals recall the good old MAST trousers. These Military Anti-Shock Garments wrapped around the patient’s abdomen and lower extremities and were inflated in patients who were in shock. The idea was that the trousers would push blood from the periphery back into the central circulation, protecting the viscera, brain, and heart. This device was introduced in the 1970s and was used until about the year 2000. You may occasionally find one if you look into old cabinets and closets around your emergency department. They are usually covered by a lot of dust. It seemed like a good idea until the literature showed it didn’t really work. It is now of historical interest only.

Does the literature examining the mechanical CPR device support its use in patients needing CPR? Or is it just going to end up in the dustbin eventually as well? In this post, I’ll talk about the origins of the mechanical CPR device. In the following posts, I’ll look at the most recent literature on how well they work.

The mechanical CPR device was first introduced in 1961. It was a framework designed to fit over a standard hospital stretcher. A source of compressed gas drove a spring-loaded piston onto the patient’s sternum with about 60 lbs. of force. Another group modified this concept by using a portable pneumatic pump to perform compressions.

By 1965, these devices were becoming more “streamlined.” Nachlas and Siedband developed a smaller version that was powered by an oxygen tank, which they believed would eventually fit on an ambulance.

Research on these devices continued through the 1970s, and a few even became commercially available. A set of published standards in 1974 commented on both manual and mechanical chest compression devices. They recommended that only well-trained and experienced personnel operate them. Furthermore, they indicated that their performance was comparable to manual CPR. However, the literature they this was based on was unclear.

These devices dropped off the radar in the 1980s, and interest was rekindled in the 1990s. Ultimately, widespread adoption of commercial devices occurred in the early 2000’s and they enjoy widespread use today.

In my next post, I’ll examine a large study published just last week examining the impact of Mechanical CPR devices on survival after cardiac arrest.

References:

  1. A history of mechanical devices for providing external chest compressions. Resuscitation 2007;73(3):330-336. doi: 10.1016/j.resuscitation.2007.01.002.
  2. Standards for Cardiopulmonary Resuscitation (CPR) and Emergency Cardiac Care (ECC). JAMA 1974;227;(7):833-868. doi:10.1001/jama.227.7.833

Artificial Platelets Under Development!

Uncontrolled bleeding is the bane of trauma professionals everywhere. Early in a resuscitation, we focus on identifying potential sources. We’ve developed numerous techniques for plugging them up. And we have processes in place to replace the blood that’s been lost.

Unfortunately, blood products are a perishable item. Packed red blood cells have a typical shelf-life of 42 days. Whole blood lasts only 21-35 days. Plasma is only suitable for up to five days once thawed. However, it can be frozen and used only when needed.

Platelets are another short-lifespan product, typically lasting only five days. This is a major reason for the relative lack of availability, especially at smaller hospitals. Unfortunately, freezing them or attempting cold storage renders them less active. For this reason, the platelet shortage persists.

As you know, platelets are fragments of cells produced by the bone marrow that have a major function in hemostasis. They bind to injured surfaces of disrupted blood vessels. Seconds later, they become activated and begin to clump with other platelets. They also release factors that result in fibrin deposition, creating a clot that helps stop bleeding.

Researchers have been trying to develop artificial blood substitutes for decades. I remember reading about rat experiments using these products in the 1980s. Unfortunately, they remain experimental to this day.

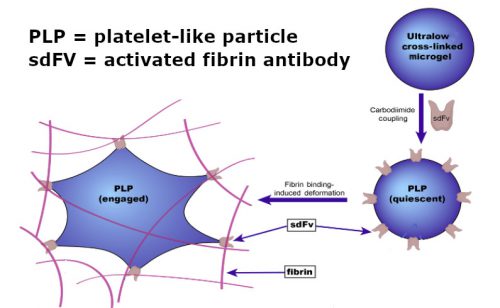
I found a recent article describing recent work on artificial platelets that piqued my interest. It was published by the biomedical engineering groups at North Carolina State University and UNC Chapel Hill. They used nanoparticles made of an ultrasoft microgel that were similar in size and shape to natural platelets. Fibrin-binding antibody fragments were embedded on the surface. These were selected to target only activated fibrin and not circulating fibrinogen.

Source: Science Translational Medicine

The groups devised a rat and pig trauma model by creating a liver laceration and then infusing varying doses of the artificial platelets (AP). Postmortem analysis of the wounds showed:

  • The APs did home in on the injured sites and were found in the injured areas
  • There was increased fibrin deposition at the wound site when compared to saline controls
  • Less bleeding was seen in the animals that received the APs vs saline
  • No significant deposition of APs was found in other tissues
  • The APs were excreted in the urine of the animals

Bottom line: This is very exciting, if preliminary, work. These artificial platelets are relatively easy to produce and can be frozen or stored at room temperature for extended periods. They appear harmless to the animals and decrease bleeding from the liver injury.

I am still somewhat cautious in my assessment. This same excitement was present 40 years ago in the early years of artificial hemoglobin solutions. And look where we are now. But, fingers crossed, there may be a solution to our chronic platelet shortage at some point in the future.

Reference: Ultrasoft platelet-like particles stop bleeding in rodent and porcine models of trauma. Sci Transl Med. 2024 Apr 10;16(742):eadi4490. doi: 10.1126/scitranslmed.adi4490. Epub 2024 Apr 10. PMID: 38598613.

First, There Was REBOA, And Now… GROA?!

REBOA (Resuscitative Endovascular Balloon Occlusion of the Aorta) is a “newer” resuscitative technique that has actually been around since the Korean War. It was first used to treat two injured soldiers, and although they ultimately died, it spurred research into the technique and its applications.

Balloon occlusion techniques were then adopted by vascular surgeons and were found to be useful as an adjunct in managing ruptured abdominal aneurysms. A slow trickle of studies on human use in trauma began to surface. But when autopsy studies carried out during the Gulf War showed that uncontrolled torso hemorrhage was a major cause of death, research in the technique exploded.

First, there were a rash of pig studies evaluating the feasibility of using a percutaneously placed occlusion device in the early 2010s. This transitioned to human studies around 2014, and after that we were off to the races. Over 100 papers on REBOA are now published each year.

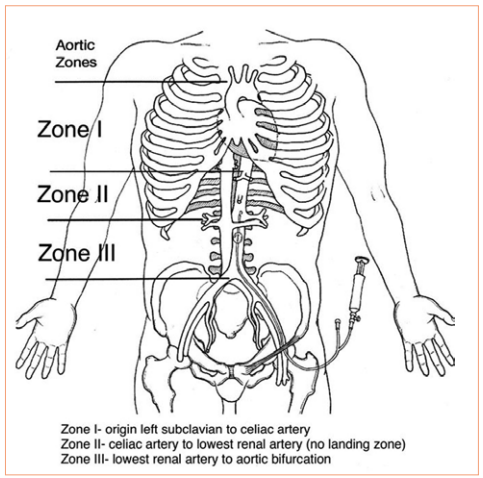
REBOA has been shown to have some advantage in patients with abdominal or pelvic sources of bleeding. The catheter is inserted in the groin and the balloon inflated in one of two zones, depending on the location of the hemorrhage (see diagram below). For abdominal bleeding, it is inserted just above the diaphragm in Zone I. For pelvic bleeding, it is inserted below the takeoff of the visceral arteries and above the aortic bifurcation, in Zone III.

In the US, REBOA catheters are only inserted upon arrival to the hospital. There are a few random reports of field placement where a physician is part of the prehospital team. By definition, this technique is generally not available in austere environments, only upon arrival in the emergency department.

Researchers at the University of Michigan began looking for an alternative technique that could be applied in the field by non-physicians. They noted the close anatomic relationship of the distal esophagus, proximal stomach, aorta, and thoracic vertebrae, and designed a device to compress the aorta against the spine in this area.

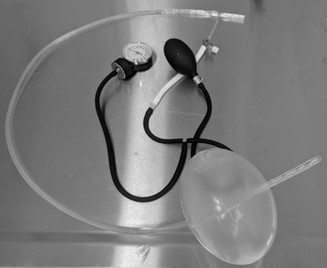
They developed a prototype device which they named GROA (gastro-esophageal resuscitative occlusion of the aorta). It consists of a gastro-esophageal tube with an ovoid balloon, an air pump with pressure measurement device, and an external compression device. Here is a picture of the device:

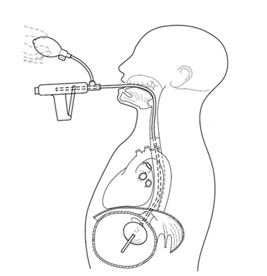
And here’s a diagram of what it looks like when inserted:

The tube is inserted and the balloon inflated. The external compression device is then placed around the patient, with the top plate located over the epigastrium and the bottom plate under the patient. It is designed to apply anterior pressure over the balloon, but to avoid circumferential constriction of the abdomen.

Bottom line: This device is an interesting development in the balloon occlusion space. As with early studies of REBOA, GROA is currently being investigated using a pig model. If it appears to be beneficial, it will still be several years before it makes the jump to human subjects. If effective, this concept would allow prehospital providers to apply some degree of hemorrhage control when it originates in the abdominal cavity.

There are currently exactly three papers on this new technique, and I have included the references below if you are interested in reading them. I’m sure there are many more to come and it may eventually be competing with REBOA for journal space.

There is one consideration to be aware of when reading these papers that is similar to much of the research on REBOA. Two of the authors have a financial interest in the company that licenses the GROA technology. And in the most recent study, another one of the authors is an advisory board member for one of the manufacturers of REBOA catheters. For these reasons, it is less likely that they will publish papers that are not favorable to the product. So read critically!

References:

  • Gastroesophageal resuscitative occlusion of the aorta: Physiologic tolerance in a swine model of hemorrhagic shock, Journal of Trauma and Acute Care Surgery: December 2020 – Volume 89 – Issue 6 – p 1114-1123 doi: 10.1097/TA.0000000000002867
  • Gastroesophageal resuscitative occlusion of the aorta prolongs survival in a lethal liver laceration model, Journal of Trauma and Acute Care Surgery: May 2022 – Volume 92 – Issue 5 – p 880-889 doi: 10.1097/TA.0000000000003444
  • Tandem use of Gastroesophageal Resuscitative Occlusion of the Aorta followed by REBOA in a Lethal Liver Laceration Model, Journal of Trauma and Acute Care Surgery: June 10, 2022 –  doi: 10.1097/TA.0000000000003719

Best Of EAST #1: When Is MTP Blood Use Too Much?

The 35th Annual Scientific Assembly of the Eastern Association for the Surgery of Trauma (EAST) begins in only a month! I will be there, sitting in the front row listening to all the great presentations. As usual, I have selected some of the abstracts that I find most interesting and will be sharing my thoughts on them with you over the coming weeks.

Let’s start out with a paper about the massive transfusion protocol (MTP). Blood has always been a scarce resource. And now, thanks to COVID, it is becoming even more so. Every trauma professional reading this has likely been involved in a trauma resuscitation that has used dozens of units of blood and other products. Unfortunately, most of the patients who require this much do not survive.

How does one balance the rapid use of many, many units of blood products with the (un)likelihood of survival and the impact of having less blood for other patients in your hospital or future incoming trauma patients? In other words, when does the use of additional blood become futile? Until now, there have been no real answers to these questions.

The trauma group at George Washington University did a deep dive into the TQIP database seeking some guidance on this topic. They reviewed five years of data, targeting patients who received at least one unit of blood within four hours of arrival. Four-hour and 24-hour mortality was analyzed to determine the point at which additional blood products did not improve survival.

The authors looked at the data two ways. They analyzed the results for all comers, as well as for patients who received balanced resuscitation. Balanced was defined as a red cell to plasma ratio in the range of 1:1 to 2:1. Results were controlled as best as possible for age, sex, race, highest AIS in each body region, comorbidities, advanced directives, and the type of surgery performed to control bleeding.

Here are the factoids:

  • Nearly 100,000 patient records were analyzed, and about 30,000 patients were found to have balanced resuscitation
  • In the all-comers group, mortality plateaued after 41 units at 4 hours and 53 units at 24 hours
  • In the balanced resuscitation patients, mortality plateaued at 40 units (4 hours) and 41 units (24 hours)

The authors concluded that this data should be used as markers for resuscitative timeouts to assess the plan of care.

My comments: This paper is very focused and provides some apparently straightforward results. However, it required some sophisticated statistical analysis to sift through the many variables that need to be controlled to obtain meaningful results. From reading the abstract, it appears that they did a good job of this.

I believe the lower number of units needed by 24 hours in the balanced resuscitation group demonstrates the benefit of getting the MTP ratios right. Non-balanced resuscitation is less efficient / effective and requires the use of more products to hit the mortality plateau.

This paper supports my opinion that a resuscitation timeout is a useful tool in helping us protect our valuable blood product resources and ensuring availability for as many patients in need as possible. What would this look like? Here are my thoughts:

  • Assign one person to monitor the MTP process in real-time. This obviously cannot be the surgeon or a member of the anesthesia team. Or even the operating room crew, as everyone will be very busy. The best practice I’ve seen is to have a dedicated trauma nurse or APP in the ED/OR recording the process on a specialized form and directing which units to give to keep the resuscitation balanced.
  • Call a timeout when the magic threshold is reached. This paper suggests that 40 is a good number.
  • Require that another trauma surgeon come into the room and review the patient condition, operative findings, and progress thus far. The two surgeons should then come to a consensus regarding utility vs futility of further surgery. Based on that decision, the operative procedure either continues or stops.
  • If the operation is to continue, then more timeouts should occur after a defined number of additional products are given.

Here are my questions for the authors / presenter:

  • The statistical analysis required is fairly advanced. Please explain in simple language why the specific regression analysis with bootstrapping was selected.
  • How do you envision applying the thresholds discovered in your paper?

This is an exciting paper and provides important information about the MTP process. I’m looking forward to hearing it in person!

Reference: CRESTING MORTALITY: DEFINING A PLATEAU IN ONGOING MASSIVE TRANSFUSION, EAST 25th ASA, oral abstract #14.