Category Archives: Resuscitation

Is The Mechanical CPR Device The Next MAST Trousers? Part 3

In my last two posts on this topic, I provided the history of the development of a mechanical CPR device. I also discussed a recent study examining a very large patient population and comparing survival with and without this device. The punchline was that it did not improve 30-day hospital survival or meaningful neurologic survival when used.  Today I’ll look at a few randomized controlled studies and then finish with a Cochrane review on the topic.

The first paper I’ll discuss is the PARAMEDIC trial published in 2014. This study was conducted in non-traumatic arrests in the UK, where ambulance service vehicles were randomly assigned to use a mechanical CPR device versus regular CPR. This intent-to-treat study used 30-day survival as its primary outcome.

A total of 4,471 patients were enrolled with a 1:2 ratio between the mechanical and manual CPR groups. Survival was 6% in the mechanical CPR group and 7% in the manual CPR group. There was no statistically significant difference. There were no serious adverse events in the manual CPR group, but some events did occur in the mechanical group, including chest bruising, lacerations, and blood in the mouth. Mechanical CPR did not confer a survival advantage in this study. 

The next study was the LINC randomized trial published in JAMA, also in 2014. It was a multi-center randomized clinical trial of patients suffering from out-of-hospital cardiac arrest in ambulance services in several European countries. The mechanical CPR recipients also underwent defibrillation if appropriate. The authors measured four-hour survival, survival up to six months, and good neurological outcome.

Four-hour survival was 24% in patients with mechanical CPR and 24% in patients with manual CPR. Survival at 6 months with good neurological outcome was 8.5% vs 7.6%, respectively. Looking at the patients who survived for six months from the flip side, good neurologic outcome was present in 99% of the mechanical CPR group and 94% of the manual group. None of these results were statistically significant. Again, there was no significant improvement in clinical outcomes with the mechanical CPR device

Finally, the Cochrane group reviewed eleven existing studies in 2018. They included nearly 13,000 adult patients who suffered either an out-of-hospital or an in-hospital cardiac arrest. Trauma patients were excluded. The overall quality of the studies was judged to be moderate to low due to the considerable risk of bias.

This review concluded that the evidence does not suggest that mechanical CPR devices are superior to conventional therapy. Some of the data reviewed indicate that there may be an increased risk of harm from using this device.

Bottom line: So what does all this mean? Overall, the idea that using a mechanical device to provide continuous, high-quality CPR to improve patient outcomes doesn’t really hold true. Good, old-fashioned manual CPR does just as well. And the mechanical units sold today retail for about $20,000 each. Are they worth the money?

The answer is… maybe. When continuous manual CPR is difficult because few pre-hospital providers are available in the field, automating CPR can be very handy. In some circumstances, such as hypothermia, CPR may need to be continued for an extended period of time. This will burn through numerous humans in a relatively short period of time. It can also be helpful when patients must be moved between different hospital areas or while preparing to place a patient on cardiac bypass. 

Each organization that purchases these units needs to carefully consider how they will use them and how they fit with the resources they have available. Only then can they do the appropriate cost-benefit analysis to see whether it makes sense, given that it seems to have no impact on survival or neurologic outcome. 

And when it comes to CPR in trauma patients, things become very hazy. Major trauma patients are either dying from a fatal brain injury or they are bleeding to death. The use of manual or mechanical CPR has no impact on either of these. 

References:

  1. Mechanical versus manual chest compression for out-of-hospital cardiac arrest (PARAMEDIC): a pragmatic, cluster randomised controlled trial. Lancet. 2015 Mar 14;385(9972):947-55. doi: 10.1016/S0140-6736(14)61886-9. Epub 2014 Nov 16. PMID: 25467566.
  2. Mechanical Chest Compressions and Simultaneous Defibrillation vs Conventional Cardiopulmonary Resuscitation in Out-of-Hospital Cardiac Arrest: The LINC Randomized Trial. JAMA. 2014;311(1):53–61. doi:10.1001/jama.2013.282538.
  3. Mechanical versus manual chest compressions for cardiac arrest. Cochrane Database Syst Rev. 2018 Aug 20;8(8):CD007260. doi: 10.1002/14651858.CD007260.pub4. PMID: 30125048; PMCID: PMC6953326.

Is The Mechanical CPR Device The Next MAST Trousers? Part 2

In my last post, I provided information on the history of the mechanical CPR device. Today I’ll examine the results of a paper published just two weeks ago that studied the rates of favorable neurological survival and overall survival to discharge in patients treated with this device.

A small group of researchers from St. Luke’s Hospital in Kansas City, Emory University in Atlanta, and the University of Texas Southwestern in Dallas performed this study. It was a seven-year, observational cohort study that used the Cardiac Arrest Registry to  Enhance Survival database. This is a prospective, multicenter registry of patients with out-of-hospital cardiac arrest in the U.S. It has a large catchment area of 200 million residents, representing about 60% of the U.S. population.

To evaluate the impact of using a mechanical CPR device for these patients, the agencies evaluated had to have submitted two or more years of data before they started using it. The researchers then evaluated whether introducing the mechanical CPR device was associated with higher survival to discharge or favorable neurological survival.

Here are the factoids:

  • The control group consisted of nearly 52,000 patients, involving 73 EMS agencies. They did not adopt the use of the device during the study period. Simple trends over time were studied.
  • The study group was 49 agencies with 32,000 patients that did begin using the device.
  • Overall favorable neurologic survival ranged from 9.6% to 10.6%, and survival to discharge ranged from 11.1% to 12.0% in the control group. These were not significant differences. It suggests there was no long-term change in these rates due to other factors.
  • In the study group, favorable neurologic survival was 8.9% before mechanical CPR device use, and 8.3% after. This was not a significant difference.
  • Also in the study group, survival to discharge was 11.0% before and 10.0% after. This was not a significant difference.
  • There were no improved outcomes between agencies that used the devices heavily, or if 911-witnessed arrests were included.

The authors concluded that EMS agency rates of favorable neurologic survival and survival to discharge were not any higher at agencies that started using mechanical CPR devices.

Bottom line: This study shows no improvement in two kinds of survival among patients treated by EMS agencies that adopted the mechanical CPR device. It did not evaluate the quality of the CPR applied. However, this is implied in the reason for using this device and the marketing materials provided by the manufacturers. 

This paper provides strike one for using the mechanical CPR device to improve survival. In my next post, I’ll review several smaller randomized clinical trials looking at the impact of these devices. Then I’ll finish up with an analysis of a Cochrane Systematic Review on the benefit of this device. 

Reference: Mechanical CPR Device Use and Cardiac Arrest Survival in EMS Agencies. Circulation. 2026 Aug 11;154(6):532-541. doi: 10.1161/CIRCULATIONAHA.126.079272. Epub 2026 Jun 18. PMID: 42312381; PMCID: PMC13286238.

Is The Mechanical CPR Device The Next MAST Trousers? Part 1

It’s very common to see major trauma patients arriving in the trauma bay with a mechanical CPR device strapped to their chest, pounding away. How did this idea start? How effective are they? As you know, anything entrenched in our daily practice to the point that we don’t even question it is fair game for scrutiny in this blog.

I’ve seen these devices used in my trauma patients for about 20 years. They keep getting sleeker and smaller, so I wanted to look at the backstory of these tools.

Why do we even need something like this? Well, there are a few things that we are fairly certain of. First, the survival rate after an out-of-the-hospital cardiac arrest is dismal. Many well-accepted studies estimate survival at about 10%. Second, we also have good data that CPR improves survival in out-of-hospital cardiac arrest. If bystanders start CPR within one minute of arrest, survival to discharge from the hospital increases to 22%. Of course, it decreases as the time interval to start it increases.

We also know that CPR quality can vary based on provider training, fatigue, hand placement, compression depth, and other factors. I’m not aware of any papers that have quantified this. In contrast, mechanical CPR machines provide constant, high-quality compressions and do not get tired. These compressions can be continued indefinitely.

It would seem logical, then, that providing continuous, high-quality CPR is a good thing. But a few of us seasoned trauma professionals recall the good old MAST trousers. These Military Anti-Shock Garments wrapped around the patient’s abdomen and lower extremities and were inflated in patients who were in shock. The idea was that the trousers would push blood from the periphery back into the central circulation, protecting the viscera, brain, and heart. This device was introduced in the 1970s and was used until about the year 2000. You may occasionally find one if you look into old cabinets and closets around your emergency department. They are usually covered by a lot of dust. It seemed like a good idea until the literature showed it didn’t really work. It is now of historical interest only.

Does the literature examining the mechanical CPR device support its use in patients needing CPR? Or is it just going to end up in the dustbin eventually as well? In this post, I’ll talk about the origins of the mechanical CPR device. In the following posts, I’ll look at the most recent literature on how well they work.

The mechanical CPR device was first introduced in 1961. It was a framework designed to fit over a standard hospital stretcher. A source of compressed gas drove a spring-loaded piston onto the patient’s sternum with about 60 lbs. of force. Another group modified this concept by using a portable pneumatic pump to perform compressions.

By 1965, these devices were becoming more “streamlined.” Nachlas and Siedband developed a smaller version that was powered by an oxygen tank, which they believed would eventually fit on an ambulance.

Research on these devices continued through the 1970s, and a few even became commercially available. A set of published standards in 1974 commented on both manual and mechanical chest compression devices. They recommended that only well-trained and experienced personnel operate them. Furthermore, they indicated that their performance was comparable to manual CPR. However, the literature they this was based on was unclear.

These devices dropped off the radar in the 1980s, and interest was rekindled in the 1990s. Ultimately, widespread adoption of commercial devices occurred in the early 2000’s and they enjoy widespread use today.

In my next post, I’ll examine a large study published just last week examining the impact of Mechanical CPR devices on survival after cardiac arrest.

References:

  1. A history of mechanical devices for providing external chest compressions. Resuscitation 2007;73(3):330-336. doi: 10.1016/j.resuscitation.2007.01.002.
  2. Standards for Cardiopulmonary Resuscitation (CPR) and Emergency Cardiac Care (ECC). JAMA 1974;227;(7):833-868. doi:10.1001/jama.227.7.833

In-House Trauma Surgeon Call – Worth It?

Nearly universally, trauma surgeons at Level I and Level II trauma centers must be at the bedside within 15 minutes of the patient’s arrival. For most, this means that they must take in-house call. This requirement has been on the books for decades. It’s just the way we do it. And that makes it fair game to examine whether it is worth the extra work.

An older prospective comparison of two Level I centers (1990) reported no difference in care timing or clinical outcomes when surgeons taking call from home lived within 15 minutes of the hospital, received reliable paging activation, and responded promptly (reference 1). Unfortunately, these days, most surgeons cannot get to the hospital within 15 minutes at night unless they arrive in their pajamas.

A large 2003 retrospective study found no difference in mortality, time to OR, CT timing, or length of stay. However, this study depended on the presence of senior surgical residents in-house to provide initial care for the trauma patient until the attending surgeon arrived (reference 2).

The best study we have so far comes from a systematic review and meta-analysis by a trauma group in the Netherlands. It included 16 observational studies in the systematic review and 8 studies in the meta-analysis, involving nearly 65,000 trauma patients (reference 3). All papers compared patients treated by in-house surgeons with those treated by surgeons on call off campus. They only looked at the impact of the coverage model on mortality.

Here are the factoids:

  • The meta-analysis showed a statistically significant risk-reduction of 14% in the patients managed by an in-house surgeon
  • There was a further mortality reduction noted in more recent papers, with an overall reduction of 17%
  • When five of the 16 papers identified as having severe bias were removed, the mortality decreased even further by a total of 19%
  • Mortality was reduced at low-volume centers with in-house surgeons by 15%

Bottom line: I have been taking in-house trauma call for 40 years. It was interesting and exciting at first, but began to wear on me over time. My impression was that in 95% of the patients that I treated, the survival die was already cast. They were destined to live or die, and little that I could do would change that. However, that remaining 5% included the patients that I would look at afterward and think to myself, “If I hadn’t been here, we would have lost them.” 

This review article bears this out, but it only addresses mortality rates. I’m fairly certain that several other, more subtle processes are also improved. For now, trauma patients who need the highest level of care clearly benefit from having a trauma surgeon at their side upon arrival. Is taking call in-house the answer? If arriving at the bedside within the 15-minute limit can be accomplished from home with a short drive time (and sleeping in scrubs), the results should be the same. The key is having the surgeon present and ready to control life-threatening hemorrhage within minutes of their arrival. However, in most urban and suburban centers, the only way to guarantee this is to stay in the hospital.

References:

  1. In-house versus on-call attending trauma surgeons at comparable level I trauma centers: a prospective study. J Trauma. 1999 Apr;46(4):535-40; discussion 540-2. doi: 10.1097/00005373-199904000-00001. PMID: 10217215.
  2. The presence of in-house attending trauma surgeons does not improve management or outcome of critically injured patients. J Trauma. 2003 Jul;55(1):20-5. doi: 10.1097/01.TA.0000071621.39088.7B. PMID: 12855876.
  3. In-house versus on-call trauma surgeon coverage: A systematic review and meta-analysis. J Trauma Acute Care Surg. 2021 Aug 1;91(2):435-444. doi: 10.1097/TA.0000000000003226. PMID: 33852558.

Liquid Plasma vs FFP: Impact On Your Massive Transfusion Protocol

In my last post, I discussed the growing number of choices for plasma replacement. Today I’ll look at some work that tried to determine whether any one of them is better than the others when used in the massive transfusion protocol (MTP).

As noted last time, fresh-frozen plasma (FFP, frozen within 8 hours) and frozen plasma (FP, frozen within 24 hours) have a shelf life of 5 days once thawed. Liquid plasma (never frozen, LQP) is good for the 21 days after the original unit was donated, plus the same 5 days, for a total of 26 days.

LQP is not used at most US trauma centers. It is more commonly used in Europe, and a study there suggested that the use of thawed plasma increased short-term mortality when compared to liquid plasma. To look at this phenomenon more closely, a group from UTHSC Houston and LSU measured hemostatic profiles in both plasma types at various time points during their useful lives.

All products were analyzed using thromboelastography (TEG) and thrombogram, and platelet count, microparticles, clotting factors, and natural coagulation inhibitors were measured. They chose 10 units of thawed FFP and 10 units of LQP, and assayed them every 5 days during their useful shelf life.

Here are the factoids:

  • Platelet counts were much higher in day 0 LQP (75K) vs day 0 thawed plasma (7.5K). Even at the end of shelf life, the LQP was 1.5x higher than thawed (15K vs 10K).
  • Thrombogram showed that LQP had higher endogenous thrombin production until the end of shelf life
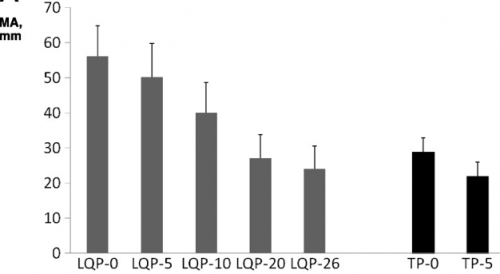
  • TEG demonstrated that LQP had a higher capacity to clot that gradually declined over time. It became similar to thawed plasma at the end of its shelf life.
                         (TEG MA for liquid (LQP) and thawed (TP) plasma
  • Most clotting factors remained stable in LQP, except Factors V and VIII, which slowly declined

Bottom line: Liquid plasma sounds like good stuff, right? Although there are a few flaws in the collection aspect of this study, it provides good evidence that never-frozen plasma has better coagulation properties than thawed plasma. Will this translate into better survival when used in the MTP for trauma? One would think so, but you never really know until you try it. Our hospital blood bank infrastructure isn’t prepared to handle this product yet, for the most part. What we really need is a study that shows the survival advantage of using liquid plasma compared to thawed plasma. But don’t hold your breath. It will take a large number of patients and some fancy statistical analysis to demonstrate this. I think we’ll have to look to our military colleagues to pull this one off!

Reference: Better hemostatic profiles of never-frozen liquid plasma compared with thawed fresh frozen plasma. J Trauma 74(1):84-91, 2013.