
Tag Archives: how to

How To: Retrograde Urethrogram

The retrograde urethrogram is one of the few diagnostic tests without a fancy CT or advanced diagnostic imaging replacement. Typically, the trauma professional calls the radiologist to perform this test. But it’s so easy, really, anyone could do it!

One of the hallmarks of urethral injury is blood at the meatus in males. The standard answer to the question “how do you evaluate for it?” is “retrograde urethrogram.” Unfortunately, too few people know how to perform this test, and not even all radiologists are familiar with it. Many times it falls to the urologist, who may not be immediately available.

Now, there is an actual instrument for this. It looks like an instrument of torture, with metal prongs to grasp the penis, a screw-down mechanism that inserts a tip into the meatus, and a connector for injecting the contrast. I actually found one of these in an unused drawer in the back of a fluoroscopy room!

Urethrogram clamp

I’ve come up with a much simpler technique. It’s a variation on the standard technique using easily to find equipment. The following items are needed:

  • A urine specimen cup
  • A tube of KY jelly (not the little unit dose packs)
  • A bottle of renografin or ultravist contrast
  • A 50-60 cc Toomey syringe (slip-tip)
  • A fluoroscopy suite

Pour 25cc of contrast and 25cc of KY jelly in the specimen cup, cap it and shake well. Draw the contrast jelly up into the syringe. Under fluoro, insert the tip of the syringe into the penis and pull the penis toward yourself, patient left or right, pinching the meatus around the tip of the syringe. This maneuver takes the contrast image away from the midline where it may interfere with imaging the more proximal urethra. Slowly inject all the contrast, watching the contrast column on the fluoro screen. Once there is easy flow into the bladder, you can stop the study. If you see extravasation into the soft tissues at any time, stop the study immediately and call Urology.

The advantages to using this technique are:

  • The contrast/jelly mix creates a thicker contrast gel that is less likely to leak from the meatus when injected
  • The jelly makes it easy to insert the catheter if no urethral injury is detected or if the lesion is incomplete and the urologist wants to insert a catheter

Normal urethrogram: see how pulling the penis to the side yields a clear image.

Normal urethrogram

Abnormal urethrogram: see the irregular puff of contrast extravasating into the soft tissues, but some urethral continuity allowing contrast to get to the bladder.

Abnormal urethrogram

How To: The Serial Abdominal Exam

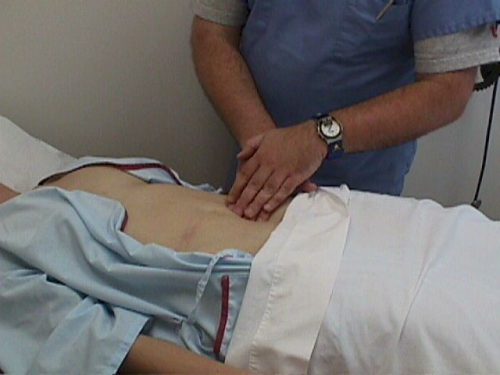
How often have you seen this in an admitting history and physical exam note? “Admit for observation; serial abdominal exams.” We say it so often it almost doesn’t mean anything. And during your training, did anyone really teach you how to do it? For most trauma professionals, I believe the answer is no.

Yet the serial abdominal exam is a key part of the management of many clinical issues, for both trauma patients as well as those with acute care surgical problems.

Here are the key points:

  • Establish a baseline. As an examiner, you need to be able to determine if your patient is getting worse. So you need to do an initial exam as a basis for comparisons.
  • Pay attention to analgesics. Make sure you know what was given last, and when. You do not need to withhold pain medications. They will reduce pain, but not eliminate it. You just need enough information to determine if the exam is getting worse with the same amount of medication on board.
  • Perform regular exams. It’s one thing to write down that serial exams will be done, but someone actually has to do them. How often? Consider how quickly your patient’s status could change, given the clinical possibilities you have in mind. In general, every 4 hours should be sufficient. Every shift is not. And be thorough!
  • Document, document, document. A new progress note should be written, dated and timed, every time you see your patient. Leave a detailed description of how the patient looks, vital signs, pertinent labs, and of course, exact details of the physical exam.
  • Practice good handoffs. Yes, we understand that you won’t be able to see the patient shift after shift. So when it’s time to handoff, bring the person relieving you and do the exam with them. You can describe the pertinent history, the exam to date, the analgesic history, and allow them to establish a baseline that matches yours. And of course, make sure they can contact you if there are any questions.

How To: Insert A Small Percutaneous Chest Tube

This short (10 minute) video demonstrated the technique for inserting small chest tubes, also known as “pigtail catheters.” It features Jessie Nelson MD from the Regions Hospital Department of Emergency Medicine. It was first shown at the third annual Trauma Education: The Next Education conference in September 2015, for which she was a course director.

Please feel free to leave any comments or ask any questions that you may have.

YouTube player

Related posts:
Pigtail catheters vs regular chest tubes
Tips for regular chest tubes