Category Archives: Guidelines

Why Create Practice Guidelines?

Practice guidelines are everywhere. More and more organizations have developed processes to create high quality ones. But why should we care? Do they improve what we already do?

Here are my reasons for using practice guidelines:

  • They provide a consistent way of approaching a clinical issue. Everybody working with the patient knows how things will be done, so they don’t have to remember the nuances that particular doctors or providers like.
  • They (hopefully) use the best and most valid scientific data to address the care issue, thus giving trauma professionals the opportunity to provide the best care we know of.
  • They decrease errors and complications by narrowing the number of choices available to providers.
  • They decrease waste for the same reason. For example, drawing blood every 6 hours vs daily for solid organ injuries can add up to three unneeded tests every day.
  • They provide our trainees with one good way to deal with the clinical issue. This is important when they move on to independent practice, and sometimes when taking standardized tests (boards).

Bottom line: If 10 trauma professionals deal with a given clinical problem 10 different ways, then none of them are doing it right! Develop a guideline that all of them can live with, based on current literature (if any). That way they can all be right for once, and our patients will reap the benefits.

In my next post, I’ll describe how to craft a good practice guideline.

When To Call Facial Surgery

This is a continuation of the when to call series that started last week. Facial injuries are another problem area where trauma professionals just reflexively call their plastic / ENT / OMFS surgeon for anything that happens to the face. This results in many unnecessary calls at off hours in centers that have them on call, and many unnecessary transfers in those that don’t.

The trauma group at the University of Arizona-Tucson recently published a paper that was presented at the annual meeting of the Western Trauma Association early this year. They sought to develop a facial injury guideline to standardize inter-hospital transfers for patients with facial fractures. With only a little effort, it could also be used to reduce the need for facial consultant services at higher-level trauma centers.

They retrospectively reviewed five years of data covering patients with craniomaxillofacial trauma transferred to their center. These patients were primarily transferred for the management of these injuries. The researchers analyzed the usual demographics, mode of transport, eventual ED disposition, insurance type, and hospital cost and reimbursement. Comprehensive information on what the facial service did was also reviewed.

A facial injury guideline (FIG) was developed using an expert panel of facial surgeons. They judged each incoming transfer as appropriate if the patient required immediate operation shortly after arrival, had an intervention during the hospital stay, or was admitted to a floor bed. In cases where there was no consensus on appropriateness, the presence of “alarming signs” was used as a tie-breaker for appropriateness. These generally consisted of visual disturbances, restricted eye motion, retrobulbar hemorrhage, and either a mandibular condyle neck fracture or a bilateral mandibular fracture. Transfer appropriateness was then tested against the FIG guidelines.

Here are the factoids:

  • Of the 511 patients transferred to this Level I center, half (51%) were deemed potentially unnecessary since they did not require intervention or admission
  • Of the remaining 252 patients, 54% were admitted to a floor bed, 15% had emergent surgery, and 79% underwent other intervention while in the hospital
  • Four-fifths of the potentially unnecessary transfers had a facial surgery consultation, and most were discharged from the ED with a median length of stay of six hours

Based on these findings, the FIG was finalized. Here’s the full guideline:

Click here to view the full-size guideline

And here is the algorithm that includes the alarming signs to look for:

Click here to view the algorithm with alarming signs

Bottom line: So how can you use this information?

If you are a Level III or IV trauma center / transferring hospital, first use the FIG guideline to determine if a transfer is necessary. If the interpretation requires additional information (yellow blocks), refer to the algorithm to determine if the patient exhibits alarming signs that justify transfer. Patients with “do not transfer” conditions (red blocks) should be scheduled for outpatient follow-up with the appropriate specialist.

If you are a Level I or II center with facial surgery coverage, patients with injuries in the red blocks can be followed up as an outpatient. If you really, really want to consult a specialist, do so during regular business hours, because they are most likely going to schedule the patient for an outpatient visit anyway. Patients with injuries in the green blocks, and those in the yellow blocks with alarming signs, should generate a consult immediately. All others are not urgent or emergent and can wait until morning.

Reference: Look me in the face and tell me that I needed to be transferred:
Defining the criteria for transferring patients with isolated facial injuries. J Trauma Acute Care Surg. 2025 May 9. doi: 10.1097/TA.0000000000004651. Epub ahead of print. PMID: 40341445.

When To Call Urology

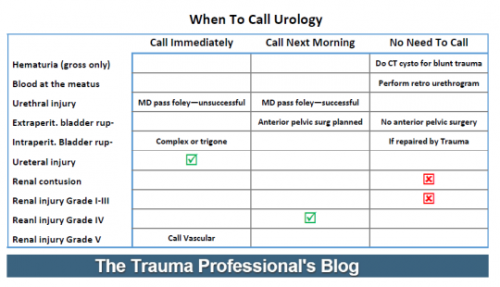
This is the second post in my series about calling your consultants wisely. The previous post focused on ophthalmology (heh heh). This one provides some useful guidance on calling your urology consultant.

This set of guidelines is concise enough to fit on an index card. The reason is that there are very few urologic injuries that can’t wait to be seen until the next day. Even simple bladder injuries (and most are) can easily be repaired by the trauma surgeon. There’s no magic to it.

In the next post, I’ll share some guidelines for managing facial injuries that were very recently published.

Click here to download the pdf file

When To Call Your Consultants

One of the growing problems in trauma care is accessing surgical subspecialists when needed. Across the US, it is getting increasingly more difficult to recruit specialists in urology, reconstructive plastic surgery, hand surgery, oral/maxillofacial surgery, and ophthalmology.

This is a challenge for all levels of trauma centers. For Level I centers, it’s primarily a recruitment issue. For Levels II-IV, it becomes a transfer issue. For all levels, the real question is, when do you really need to call them? One reason for the shortage problem is that we tend to call too much, bothering them when they are not needed.

The best practice for trauma centers of all levels is to collaborate with subspecialists and develop a practice guideline that lists commonly encountered clinical problems in their field, along with the consult and follow-up expectations for each. Frequently, a large portion of patients can go home and follow up with the subspecialist as an outpatient.

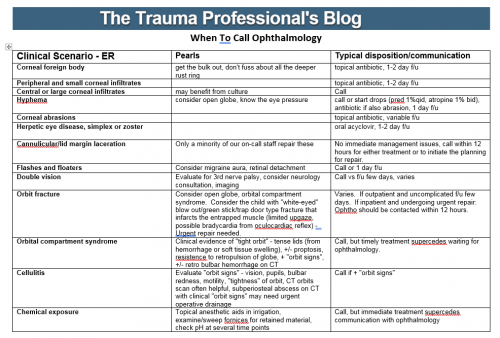
I’ve prepared several sample practice guidelines for you to use in your conversations with your own subspecialists. Today, I’ll publish my ophthalmology guideline. In the next post, I’ll cover urology. And finally, I’ll review some new guidelines for facial injuries that were recently published.

Here’s the eye guideline. You can download it by clicking on it or using the links below.

Or click this link to download

Best Practice: The MTP Coordinator

Every trauma center has a massive transfusion protocol (MTP). But every trauma center also does it entirely differently. Ideally, an MTP is designed with the resources available at the hospital in mind. These may include whole blood, the use of O- vs. O+ blood, the number of units of each product per cooler, the different products in different coolers, and personnel available to move those coolers to the correct locations.

In my experience, one of the areas with the greatest variability is the person or persons who are actually directing the blood resuscitation, hanging the units, and doing the paperwork. Frequently, this is split across several people. In the ED, the surgeon is usually directing it. However, nurses typically hang the products and do the paperwork.

Often, though, the surgeon may be up to their elbows in a resuscitative thoracotomy and may be unable to direct their full attention to figuring out if more products are needed. In the OR, the anesthesiologist can frequently take over this task while the surgeon is busy in a body cavity. But sometimes, the resuscitation needs may overwhelm even their ability to concentrate on the MTP.

The Solution

The solution to this problem borrows from the team leader concept in trauma resuscitation. It is best if the team leader has minimal clinical responsibilities during the resuscitation. Once they move in and touch the patient, their area of attention collapses to that one spot, and they cannot fully concentrate on all of the big-picture issues going on in the room.

This is where the MTP coordinator comes in. This is a dedicated person who only has one job: to deal with the MTP.  They have no other responsibilities in the room.

Here is a list of tasks that they can offload from the other nurses and physicians in the ED/OR:

  • Call for the next cooler to be sent from the blood bank, taking into account the transit time
  • Ensure required labs are being sent for crossmatch and TEG/ROTEM, if used
  • Order and hang TXA on appropriate patients
  • Transfuse products in the appropriate order
  • Fill out all required transfusion records
  • Ensure 1:1:1 transfusion ratios
  • Regularly inform the surgeon of the current product counts
  • Order calcium and cryoprecipitate when appropriate, according to your protocol
  • Inform the blood bank when the patient moves to a new area (e.g. ED to OR) and follow along with the patient
  • As the resuscitation winds down, interpret TEG/ROTEM and modify transfused products as indicated
  • Notify the blood bank when the MTP is terminated
  • Ensure all final paperwork is complete

This seems like a lot! But we are normally asking numerous people in the trauma bay to do it. Assigning it to one person and one person only creates a much more reliable and efficient system.

Who should it be assigned to? Generally, not one of the usual ED nurses. This is a specialized position that requires additional training and practice. Some trauma programs have dedicated trauma nurses for trauma resuscitation, and they may be a good choice. However, they are frequently the only nurses assigned to resuscitations, and making them the MTP coordinator takes them off all other duties. This may not be practical.

In my opinion, the best candidate is an ICU nurse who has received training for this duty. Ideally, it would be the ICU nurse who would be receiving and taking care of that patient in the ICU if they survive. They will be very familiar with their patient once they arrive there.

If you have an MTP coordinator at your center, please take a moment to leave comments or suggestions below! Let us know how you do it.