
Liver Laceration And Liver Function Tests

Over the years, I’ve seen a number of trauma professionals, both surgeons and emergency physicians, order liver transaminases (SGOT, SGPT) and bilirubin in patients with liver laceration. I’ve never been clear on why, so I decided to check it out. As it turns out, this is another one of those “old habits die hard” phenomena.
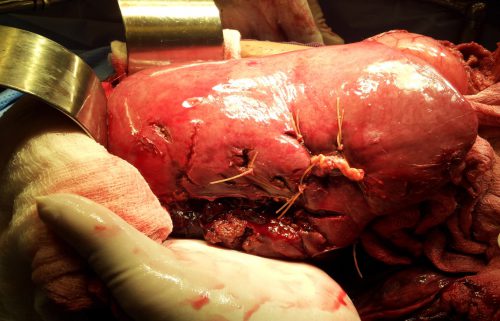
Liver lacerations, by definition, are disruptions of the liver parenchyma. Liver tissue and bile ducts of various sizes are both injured. Is it reasonable to expect that liver function tests would be elevated? A review of the literature follows the typical pattern. Old studies with very few patients.

From personal hands-on experience, the liver tissue itself tears easily, but the ducts are much tougher. It is fairly common to see small, intact ducts bridging small tears in the substance of the liver. However, larger injuries can certainly disrupt major ducts, leading to major problems. But I’ve never seen obstructive problems develop from this injury.

Several papers (very small, retrospective series) have shown that transaminases can rise with liver laceration. However, they do not rise reliably enough to be good predictors of either having an injury or the degree of injury. Similarly, bilirubin can be elevated, but usually not as a direct result of the injury. The most common causes are breakdown of transfused or extravasated blood, or from critical care issues like sepsis, infection, and shock.

Bottom line: Don’t bother to get liver function tests in patients with known or suspected injury. Only a CT scan can help you find and/or grade the injury. And never blame an elevated bilirubin on the injury. Start searching for other causes, because they will end up being much more clinically significant.

References:

  • Evaluation of liver function tests in screening for intra-abdominal injuries. Ann Emerg Med 20(8):838-841, 1991.
  • Markers for occult liver injury in cases of physical abuse in children. Pediatrics 89(2):274-278.
  • Combination of white blood cell count with liver enzymes in the diagnosis of blunt liver laceration. Am J Emerg Med 28(9):1024-1029, 2010.

Trauma Service Best Practice: The Afternoon Handoff

In my previous post, I stressed using a structured process to hand off information between the overnight trauma team and the incoming day providers. There is one more very important handoff that occurs in most centers as well: the afternoon handoff. This involves the transition between the day team, who received the morning report, and the trauma professionals who relieve them in the late afternoon or early evening.

This handoff is not nearly as involved as the morning one. Hospitals are structured to be very busy during the morning and afternoon shifts, and activity then tapers off in the evening and at night. However, a smooth transition of personnel is essential to ensure seamless patient care.

Following is the list of items I think are essential for that afternoon handoff:

  1. Introductions. This may not be necessary because the afternoon team is typically smaller than the morning report team, and the players typically know each other well.
  2. Urgent issues. This is a list of critical events that need to be addressed soon or immediately. These are typically much less common in the afternoon, but may still occur.
  3. Pending transfers in. The day team should list any scheduled transfers in from outside hospitals that have not yet arrived.
  4. Existing patient lists.  The service lists should be run at this point. Any pending work or tasks not completed by the day shift should be listed so they can be seamlessly picked up by the relief team.
  5. START THE EVENING!!

Just like morning report, this handoff should be conducted at a set time and place to develop consistency. It also allows all players to adhere to any overtime or work hour restrictions.

If your center includes other items on these checklists that you find helpful, please email or leave a comment below.

Click here to read the morning report best practice post

Trauma Service Best Practice: The Morning Report

Trauma professionals are immersed in patient care for a significant portion of their workday. They accumulate and process a lot of information about many patients during that time. But at some point, they actually get to go home!

What happens to all that knowledge from their workday? It must be shared to provide good continuity of care. So ideally, it is passed on to the team coming in to relieve them.

Many trauma centers have adopted some form of “morning report” to share knowledge from the outgoing night team with the incoming day team. In my experience, many of these meetings are relatively unstructured. They work, but they could be more effective/efficient.

A “best practice” for the morning report is to systematize it so it always includes all the key items needed for the shift transition. The best way to accomplish this is with a checklist. Pilots use these to make sure they don’t forget key tasks, such as lowering the landing gear at the right time. The same thing applies to the trauma morning report.

Here is a list of what I consider to be the key items to include in your morning report:

  1. Introductions. This is a quick round of self-introductions, with names and roles. In many trauma centers where the team is small and everyone knows each other, this step may be unnecessary. However, larger centers with large teams or frequent rotations on and off the service will definitely benefit from this step.
  2. Urgent issues. This is a list of critical events that need to be addressed soon or immediately. This could be a patient who just started crashing. Some members of the incoming team may need to leave to deal with these situations.
  3. Pending transfers in. The night team should describe any transfers they have accepted, with a summary of the patients and their known needs upon arrival.
  4. Patient phone calls. If any patient calls (i.e., from previously discharged patients) were relayed to the overnight team by the call center, these should be detailed so the a member of the day team (MD or RN as appropriate) can follow up as needed.
  5. New patient summaries. All new admissions should be presented briefly, including mechanism of injury, pertinent exam finding, workup completed, diagnoses, further studies needed, and the proposed treatment plan.
  6. Existing patient lists. Service lists should be run, and any patients that have needs that must be taken care of before rounds should be noted. Examples include a serial abdominal exam or a wound check if a possible infection is suspected.
  7. Discharge list. Hopefully, discharge planning has been ongoing during each patient’s stay. All patient discharges planned for the day should be noted so they can be examined early by a team member to ensure they are on track for leaving the hospital early in the day.
  8. Team assignments. This depends on the size of the service and the number of teams. Some personnel may be assigned to a specific service. Some may be directed to go to the OR, the ICU, or cover the clinic.
  9. START THE DAY!!

Ideally, morning report should occur at the same time every day of the week, every day of the year. Most tend to start between 6 and 8 am. If emergencies occur and morning report is interrupted, key personnel should tend to the acute problem and any remaining members continue with morning report. As soon as the emergency has ended, the incoming team members should reassemble to complete the checklist. In some situations, it may be more convenient to continue this at rounds. But be sure to cover all key items as early as possible.

Click here to read the afternoon handoff best practice post

Do I Have To Call My Trauma Team For Incoming Transfers?

All trauma centers receive transfers  from referring hospitals. Often, a portion of the workup has already been completed at that hospital. If the patient meets one or more of your trauma activation criteria, do you still need to activate your team when they arrive?

And the answer is: sometimes. But probably not that often.

Think about it. You should activate your team if you suspect the patient may have an injury requiring rapid diagnosis and treatment. The purpose of any trauma activation is speed. Rapid evaluation. Fast lab results. Quick access to CT scan or OR. If a significant amount of time has already passed (transported to an outside hospital, worked up for an hour or two, then transported to you), then it is less likely that a trauma activation will benefit the patient.

There are four classes of trauma activation criteria. I’ll touch on each one and the need to activate in a delayed fashion if present, in priority order.

  • Physiologic. If there is a significant disturbance in vital signs while in transit to you (hypotension, tachycardia, respiratory problems, coma), then you must activate. Something else is going on that needs to be corrected as soon as the patient arrives. And remember the two mandatory ACS criteria that fall into this category: respiratory compromise/need for an emergent airway, and patients receiving blood to maintain vital signs. But a patient who needed an airway who is already intubated and no longer compromised does not need to be a trauma activation.
  • Anatomic. Most simple anatomic criteria (e.g., long bone or pelvic fractures) do not need a trauma activation unless the patient is beginning to show signs of physiologic compromise. However, anatomic criteria that require rapid treatment or access to the OR (proximal amputations, mangled or pulseless extremities, spinal cord injury) should be activated.
  • Mechanism. Most of the vague mechanistic criteria (falls, pedestrian struck, vehicle intrusion) do not require trauma activation after transfer to you. But once again, if the mechanism suggests a need for further rapid diagnosis or treatment (penetrating injury to abdomen), then activate.
  • Comorbidities. This includes underlying diseases, extremes of age, and pregnancy. In general, these will not require trauma activation after they arrive.

Bottom line: In many cases, the patient transferred in from another hospital will not need to be a trauma activation, especially if they have been reasonably assessed there. The patient should be rapidly eyeballed by your emergency physicians, and if there is any doubt about their condition, activate then.

However, if little workup was done at the outside hospital (my preference), and the injuries are “fresh” (less than a few hours old), then definitely call your team. 

Survival After Penetrating Injury To The Heart

Penetrating injury to the chest, and especially the heart, has a high mortality rate. The best way to reduce mortality is rapid pre-hospital transport to a trauma center where life-saving measures can be carried out immediately. Frequently, these measures include resuscitative thoracotomy. The Western Trauma Society has a well-known guideline to help with decision-making in performing this procedure.

The trauma group at Sinai Chicago recently published a paper slicing and dicing the possible predictors of survival after cardiac injury. As I read this paper, I was curious about how this information would change our practice, especially with the decision to open the chest.

The authors performed a retrospective cohort study of patients who had suffered penetrating cardiac trauma over nine years. Here are the factoids:

  • Over 18,000 patient encounters were analyzed (average 2,000 per year), and only 57 penetrating cardiac injuries were identified (3%)
  • Overall survival was 25% (!)
  • Gunshot victims were 3.7x more likely to die
  • Mortality odds ratios for specific injury patterns were as follows:
    • Multiple cardiac chambers injured 11x
    • Thoracic vascular injury 12x
    • Concurrent abdominal injury 4.4x
  • These findings were noted to decrease the likelihood (odds ratio) of death:
    • Isolated cardiac injury 0.2x
    • Spontaneous respirations 0.06x
    • Signs of life on arrival 0.01x
  • Every patient (35) who underwent resuscitative thoracotomy died

The authors suggested that recognizing these factors could help clinicians in decision-making processes during early triage and resuscitation.

Bottom line: When I first read the paper, it seemed that this was all common-sense information and didn’t add much to our body of knowledge. However, upon closer reading, there are some good tidbits here. The work here helps identify which patients are most likely to benefit from opening the chest. It assigns probabilities to anatomic and physiologic criteria, some of which are apparent at the time of patient arrival and are available for decision making. The fact that every patient who underwent resuscitative thoracotomy died is not alarming; it merely reflects the fact that these are patients who are the sickest of the sick. 

So how do we put the information in this paper to use? The resuscitative thoracotomy algorithm from the Western Trauma Association should be utilized first. When the patient is on the cusp of the 15-minute CPR decision point, the odds ratios in this paper might be used to tilt the scales one way or the other. Does the patient also have abdominal injuries? Are there no signs of life? Then perhaps clinician judgment may dictate that the procedure not be performed. Alternatively, if the thoracotomy is carried out in patients and any of the three high-risk anatomic indicators for death are present, they might then choose to terminate the procedure to conserve resources. 

Overall, this paper does not force any major changes in care. It informs the trauma professional and allows them to couple that information with existing algorithms and care processes, so they might either further improve the patient’s probability of survival or conserve scarce resources if survival is unlikely. 

References: 

  1. Predictors of survival after penetrating cardiac trauma: injury patterns and presentation factors. Trauma Surg Acute Care
    Open 2026;11:e002237.
  2. Western Trauma Association Resuscitative Thoracotomy Practice Guideline

Home of the Trauma Professional's Blog

Do you want to get a daily email every time there’s a new post? See what I’m up to.

Click here to get details and subscribe!

[accua-form fid=”1″]

[mc4wp_form id=”2023″]