
Category Archives: General

What Is: A Morel-Lavallee Lesion? Part 1

Anyone who takes care of blunt trauma has seen the Morel-Lavallee lesion (M-L). Here’s an obvious one because it’s acute:
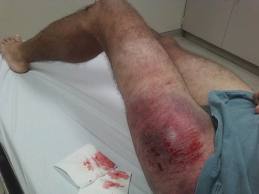
The M-L lesion is essentially a closed degloving injury in which the skin remains intact. The subcutaneous tissue is sheared off of the underlying fascia, and typically blood accumulates in the potential space that is created. This picture shows a less acute lesion; the bruising and ecchymosis on the surface have resolved. Note the collection on the lateral thigh:
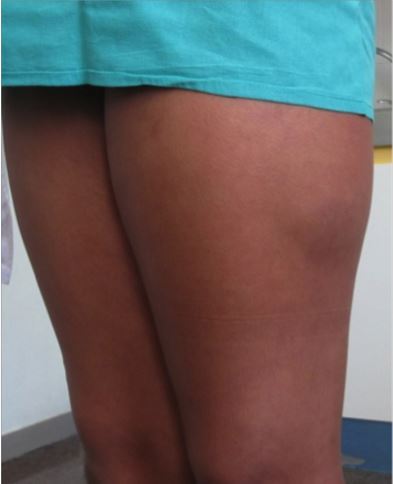
These injuries may take a very long time to resolve and may leave some residual deformity. The definitive management has never been very clear: needle drainage vs incision, timing, compression wraps, etc.

The Mayo Clinic reviewed their 8-year experience with 87 of these lesions to try to shed some light on proper management. They treated their patients in four different ways: needle drainage, incision and drainage, compression wraps, and debridement with vacuum drainage devices. Here are the factoids from their study:

  • Motor vehicle crash was the most common etiology for this lesion, which makes sense due to the energy needed to shear the tissues
  • The most common locations were thigh, hip, and flank
  • The incidence of pre-existing conditions that might influence outcome (diabetes, obesity, smoking history, use of anticoagulants) did not seem to influence outcomes
  • Lesion location did not change the recurrence rate (even over joints)
  • Aspiration suffered the highest recurrence rate (56%) vs only 15-19% in the other groups
  • Aspiration of more than 50cc of fluid was more common in lesions that recurred (83%) vs those that did not (33%)

Their experience led them to develop the following practice guideline:
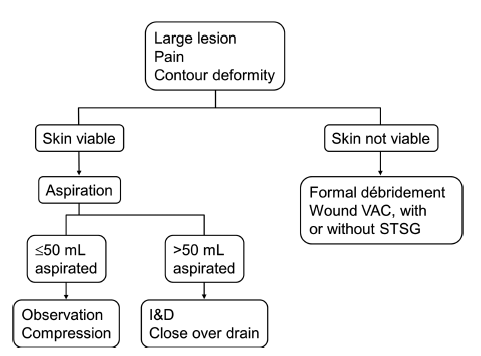
An incision and drainage procedure is not necessarily straightforward. Many of these wounds develop a pseudo-capsule if they are long-standing. Closure of the dead space can be challenging and may require quilting sutures or use of fibrin glue in addition to low suction drains. Some surgeons use sclerosing agents, either alone or in addition to the adjuncts listed above.

Bottom line: The Morel-Lavallee lesion can be challenging to treat. Although this study has limited numbers, it provides guidance to suggest a consistent way of managing it. 

In my next post, I’ll review a brand new multicenter study that provides some additional information on this troublesome wound.

Reference: The Mayo Clinic experience with Morel-Lavallee lesions: establishment of a practice management guideline. J Trauma 76(2):493-497, 2014.

Trauma Activation For Hanging: Yes or No?

In my last post, I discussed a little-reviewed topic, strangulation. I recommended activating your trauma team only for patients who met the physiologic criteria for it.

But now, what about hangings? There are basically two types. The judicial hanging is something most of you will never see. This is a precisely executed technique that involves falling from a certain height while a professionally crafted noose arrests the fall. This results in a fairly predictable set of cervical spine/cord, airway, and vascular injuries. Death is rapid.

Suicidal hangings are far different. They involve some type of ligature around the neck, but rarely include a fall from any distance. This causes slow asphyxiation and death, sometimes. The literature dealing with near hangings is a potpourri of case reports, speculation, and very few actual studies. So once again, we are left with little guidance.

What type of workup should occur? Should the trauma team be called? A very busy Level I trauma center reviewed its registry for adult near-hangings over a 19-year period. Hanging was strictly defined as a ligature around the neck with only the body weight used for suspension. A total of 125 patients were analyzed and grouped into those with a normal GCS (15) and those with an abnormal GCS (<15).

Here are the factoids:

  • Two-thirds of patients presented with normal GCS, and one-third were impaired
  • Most occurred at home (64%), and jail hangings occurred in 6%
  • Only 13% actually fell some distance before the ligature tightened
  • If there was no fall, 32% had full weight on the ligature, 28% had no weight on it,  and 40% had partial weight
  • Patients with decreased GCS tended to have full weight on suspension (76%), were much more likely to be intubated prior to arrival (83% vs 0% for GCS 15), had loss of consciousness (77% vs 35%), and had dysphonia and/or dysphagia (30% vs 8%)
  • Other than a ligature mark, physical findings were rare, especially in the normal GCS group. Subq air was found in only 12% and stridor in 18%.
  • No patients had physical findings associated with vascular injury (thrill, bruit)
  • Injuries were only found in 4 patients: 1 cervical spine fracture, 2 vascular injuries, and 1 pneumothorax
  • 10 patients died and 8 suffered permanent disability, all in the low GCS group

Bottom line: It is obvious that patients with normal GCS after attempted hanging are very different from those who are impaired. The authors developed an algorithm based on the initial GCS, which I agree with. Here is what I recommend:

  • Do not activate the trauma team, even for low GCS. This mechanism seldom produces injuries that require any surgical specialist. This is an exception to the usual GCS criterion.
  • The emergency physician should direct the initial diagnosis and management. This includes airway, selection of imaging, and directing disposition. A good physical exam, including auscultation (remember that?) is essential.
  • Patients with normal GCS and minimal neck tenderness or other symptoms do not need imaging of any kind.
  • Patients with abnormal GCS should undergo CT scanning, consisting of a CT angiogram of the neck and brain with soft tissue images of the neck and cervical spine recons.
  • Based on final diagnoses, the patient can be admitted to an appropriate medical service or mental health. In the very rare case of a spine, airway, or vascular injury, the appropriate service can be consulted.

Reference: A case for less workup in near hanging. J Trauma 81(5):925-930, 2016.

Gunshot To The Face!

You’ve just been pre-notified of an incoming trauma activation: gunshot to the face. No other information. How concerned should you be? Here are some things to think about as you wait for the patient to arrive:

  • Is it really a gunshot? Sometimes shotgun injuries are reported as gunshots. Big difference!
  • Will I need to preserve evidence? In general, yes. In most cases other than suicide attempts, there is probably a good chance that criminal activity was involved. Be prepared to preserve all patient belongings in paper bags, and have a chain of custody form available.
  • Am I and my team safe? There is a possibility that someone wants your incoming patient dead. They may want to finish the job, in you emergency department. Make sure the area is secure.

Once the patient arrives, it’s best to think through things via the ATLS framework.

  • Airway. If the injury involves the lower part of the face or neck, make sure the airway is safe and/or secure. Blood may create problems, as can edema from injury to soft tissues, especially in the floor of the mouth.
  • Breathing. Not a problem with these injuries unless significant aspiration has occurred.
  • Circulation. The face can really bleed, and only a few areas are amenable to the usual surgical control (clamping, tying). Direct pressure must be used for the rest, and this doesn’t always work. Bleeding from sinuses may be controlled with packing or the foley catheter trick (inserted through bullet tract). But if you can’t stop it, then it’s time to expedite to the OR.
  • Disability. You do have to worry about the cervical spine if the path of the bullet is not obvious. If the patient is stable, immobilize the neck and use the CT scanner to see if any fragments involved the spine. If you must run to the OR with an unstable patient, then try to quickly shoot an old-fashioned cross-table lateral. This will give you quick and dirty info on how much you can manipulate the neck.

Related posts:

Beware The DEA Scam!

Scammers are everywhere!

I received a phone call from a phone number with the caller ID “US GOV DEA” in Manassas, Virginia. It was screened by my Robokiller robocall app, and the caller left the following message:

“Good morning, this is Officer Alan Matthew with DEA the drug enforcement administration and my ID is M as in Mary, A as in apple, number 9173. This message is for Dr. Michael McGonigal. The reason of this call is to inform you Dr. Michael is that your NPI number which is <redacted> and your medical license number which is <redacted>. Your NPI and your medical license number involved in some fraudulent activities in San Antonio, Texas and that’s the reason we are trying to reach you to make you aware about the situation. So when you receive this message if you’re not aware about this please give us a call back as soon as possible. The department direct line which is 571-532-0076. I repeat the number is 571-532-0076. Thank you so much, have a good day.”

Some people might be fooled by the caller ID, but these can very easily be spoofed. In general, the DEA, like other Federal agencies, will not contact you primarily by phone. US Mail is the preferred route. That was the first clue that this was not a legitimate call.

Next, I listened to the message. The speaker had a pronounced accent, which in and of itself is not unusual. However, his grammar was not very good. My NPI and medical license number are available from public records, so I ignored that. Interestingly, he did not recite my DEA number, which is not public.

But the caller then tried to make the situation sound urgent by saying it involved fraudulent use of these numbers. This is a classic tactic used by scammers to elicit an emotional response and cause their mark to lower their cognitive defenses.

When I did an internet search on the number, the first item that came up was:

“DEA warns of scammers impersonating DEA employees”

from June of 2020.

The DEA warns that the scanners may:

  • use an urgent and aggressive tone, refusing to speak to or leave a message with anyone other than their targeted victim
  • threaten arrest, prosecution, imprisonment, and, in the case of medical practitioners, revocation of their DEA numbers
  • demand thousands of dollars via wire transfer or, in some instances, in the form of untraceable gift cards taken over the phone
  • falsify the number on caller ID to appear as a legitimate DEA phone number
  • will often ask for personal information, such as social security number or date of birth
  • reference National Provider Identifier numbers and/or state license numbers when calling a medical practitioner. They also might claim that patients are making accusations against that practitioner.

What should you do if you receive a call like this? First, completely ignore it. Do not call the number! The DEA points out that it is a federal crime to impersonate a DEA agent, and has a reporting link on their website. However, it just provides a little more information and directs you to an FBI reporting site. This web page is geared toward reporting if you have been a financial victim. Unfortunately, I doubt the agency has the time or resources to pursue mere phone calls unless you have suffered personal or financial harm.

Bottom line: All of this is classic scam action. This has been going on for five years, and continues to this day. Don’t be fooled and fall for this scheme!