
All posts by The Trauma Pro

What Is The Zumkeller Index in TBI?

Most trauma professionals who take care of serious head trauma have already recognized the importance of quantifying extra-axial hematoma thickness (HT) and midline shift (MLS) of the brain. Here’s a picture to illustrate the concept:
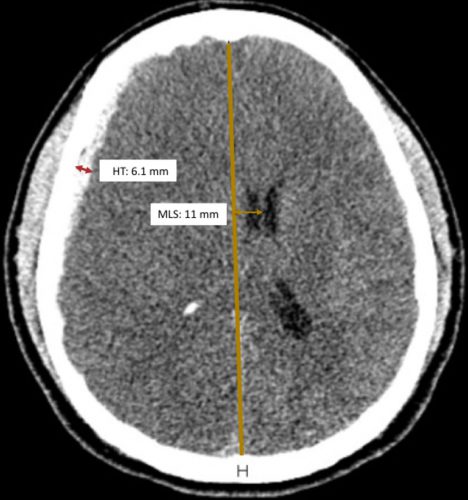
Source: Trauma Surgery Acute Care Open

Zumkeller and colleagues first described the use of the mathematical difference between these two values in prognosticating outcomes in severe TBI in 1996.

Zumkeller Index (ZI) = Midline shift (MDI) – Hematoma thickness (HT)

Intuitively, we’ve been using this all along. At some point, we recognized that if the degree of midline shift exceeds the hematoma thickness, it’s a bad sign. The easiest way to explain this is that there is injury to the brain that is causing swelling so the shift is greater than the size of the hematoma. 

The authors of the current paper from Brazil decided to quantify the prognostic value of the ZI by doing a post-hoc analysis of a previously completed prospective study.  They limited their study to adult patients with an acute traumatic subdural hematoma confirmed by CT scan. It used data from the 4-year period from 2012-2015.

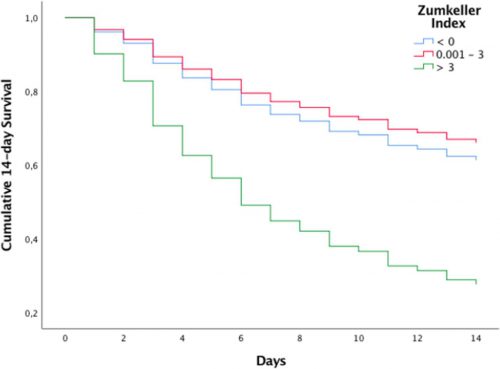
They compared demographics and outcomes in three cohorts of ZI:

  • Zero or negative ZI, meaning that the midline shift was less than the size of the hematoma
  • ZI from 0.1 mm to 3.0 mm
  • ZI > 3.0 mm

And here are the factoids:’

  • A total of 114 patients were studied, and the mechanism of injury was about 50:50 from motor vehicle crashes vs falls
  • About two thirds were classified as severe and the others were mild to moderate, based on GCS
  • Median initial GCS decreased from 6 in the low ZI group to 3 in the highest ZI group, implying that injuries were worse in the highest ZI group
  • Mortality (14-day) was 91% in the highest ZI group and only in the low 30% range in the others
  • Regression analysis showed that patients with ZI > 3 had an 8x chance of dying within 14 days compared to the others
Source: Trauma Surgery Acute Care Open

Bottom line: This study confirms and quantifies something that many of us have been unconsciously using all along: midline shift greater than the size of the hematoma is bad! Of course there are some possible confounding factors that were not quantified in this study. Patients with the more severe injuries tended to also have subarachnoid hemorrhage and/or intra-ventricular blood. Both are predictors of worse prognosis. But this is a nice study that quantifies our subjective impressions.

The Zumkeller Index is an easily applied tool using the measuring tool of your PACS application. It can be used to determine how aggressively to treat your patient, and may help the neurosurgeons decide who should receive a decompressive craniectomy and how soon.

Reference: Mismatch between midline shift and hematoma thickness as a prognostic factor of mortality in patients sustaining acute subdural hematomaTrauma Surgery & Acute Care Open 2021;6:e000707. doi: 10.1136/tsaco-2021-000707

The Value Of Bowel Sounds In Acute Trauma Evaluation

Universally, trauma professionals are taught how to listen for bowel sounds during their training. And most healthcare professionals these days still listen for them during routine examinations. But remember, if you find yourself saying “that’s the way we always do it,” be careful!

Yes, we’ve been taught to perform this examination literally for centuries. But is it valuable? No one seems to ask that question anymore. A nurse from Brighton in the UK published a review about 25 years ago that most readers are not familiar with. She performed a 10-year review of the literature, searching on the keyword “bowel sounds.” It turns out there were very few hits. The search was widened to include another 20 years, and the terms “abdominal examination” and “abdominal physical assessment.” Based on these search difficulties, you can see how much we take this skill for granted and how little has been written about it.

All told, only five papers were identified. Typical exam parameters described included the normal frequency of bowel sounds, how long to listen if no sounds are heard, the locations to auscultate, and whether to palpate first and then listen, or listen then palpate.

Frequency of normal bowel sounds. Most papers agreed that normal bowel sounds are heard between every 5-15 seconds to every 5-35 seconds. Unfortunately, the frequency can vary, making it nearly impossible to distinguish hypoactive from hyperactive bowel sounds.

How long to listen. The literature varied from 2 minutes in the right lower quadrant only (?) to 7 minutes in all four quadrants. Some suggested that if no sounds were heard, the examiner should palpate the abdomen to stimulate peristalsis.

No palpation before auscultation. This was stated in all the papers. The fear was that it would increase the frequency of bowel sounds and confuse the examiner.

Bottom line: As in much of medicine, there is little literature to truly guide us here. There is substantial variability in reported results, and considerable clinician variability even in describing whether a patient’s bowel sounds were loud or soft, hypoactive or hyperactive. Most of what we take for granted with this exam tool is based on tradition, personal preference, and anecdotal teaching.

In trauma care, I don’t believe there is any value in spending time (which we don’t have much of during a trauma resuscitation anyway) listening for bowel sounds in a noisy room. We have all taken care of patients with a gunshot to the abdomen who have bowel sounds, and a minimally injured patients who have none. The best practice is to perform a good physical inspection and palpation of the abdomen, followed by appropriate x-rays or scans. Save your stethoscope for the chest exam.

Reference: A critical review of auscultating bowel sounds. Br J Nurs. 2009 Oct 8-21;18(18):1125-9. doi: 10.12968/bjon.2009.18.18.44555. PMID: 19966732.

How Often Should My Trauma Operations Committee Meet?

In my last post, I discussed how often your multidisciplinary trauma performance improvement committee (PI) should meet. As you know, one other mandatory committee is required of all trauma centers, the Trauma Operations Committee (Ops). In this post, I will:

  • describe how often your operations committee should meet
  • help you determine whether your two committees should meet on the same day or separately

How Often?

The short answer to this question is practically the same as for your PI committee, “It depends.” Whereas the PI committee schedule is determined more by the volume of your performance improvement activity, your ops committee is driven by its agenda.

First, look at what items are on your typical agenda:

  • Reports
  • Announcements
  • Policy discussion and revision
  • Marketing and outreach planning
  • TQIP report analysis
  • System issue analysis
  • Workgroup reports
  • Other stuff

Now, think back to your previous meetings. Do you sometimes have to cancel due to a lack of agenda items? Do you struggle to keep to the time allotted and frequently go over it? These are your biggest clues that let you know that you need to adjust the meeting frequency,

In general, your ops committee frequency is reasonably predictable from your trauma center level:

  • Level I – monthly
  • Moderate to high volume Level II – monthly
  • Lower volume Level II – bimonthly
  • Level III – bimonthly to quarterly
  • Level IV – quarterly

However, the agenda is really what drives meeting frequency. If you have a very active ops committee or are a “young” trauma center, this group may be very busy and need to meet more frequently than this. Base your final decision on your level of “busyness.”

To Combine Or Not Combine?

Combining your PI and Ops committee meetings has several pros and cons.

  Pros:

  • Decreases the number of meetings for everybody by one
  • Easier scheduling for attendees and venue
  • Consolidates agenda planning for the trauma admin team

  Cons:

  • May lead to loooong meetings
  • Frequently results in a less predictable start time for the second meeting
  • Requires extra administrative effort to maintain separate minutes and content
  • Often involves required attendees changing between meetings

Consider the logistics and personalities involved in your committees carefully. Do the attendees value shorter meetings with a predictable start time? Or do they just want to power through and take care of all of the business at hand?

Bottom line: First, determine the ideal frequency for your operations committee meeting. Is it the same as your PI committee? If so, consider combining them. If not, you will probably be forced to live with separate meetings. It is possible, however, to be creative. Consider a monthly PI meeting combined with the Ops meeting every other month.

What is the usual combined duration of the two meetings? If it is more than 2 hours, I recommend not combining them. That is just too long for your attendees to stay focused. If you can combine them, then look at the specific attendees for each meeting. Are they mostly the same? If they are, you are more likely to be successful when combining them. Reach out to your attendees to see if they would welcome a single meeting date and time. But warn them that it will routinely be 1.5 to 2 hours in length.

Now, plan your agendas carefully. If you have a substantial number of attendee changes between meetings, figure out how people will know when to show up for the second. It is easiest to have the smaller meeting first, and then add attendees when the second one starts. As for timing, there are two choices: always make each meeting a fixed length, or limit your first meeting to an exact length and allow the second to start at a fixed time and have a variable duration.

Finally, make sure the contents and minutes of the two meetings are separate. This keeps your documentation clean and easier to follow.

How Often Should My Trauma Multidisciplinary Performance Improvement Committee Meet?

Every trauma center is required to have two specific committees: a multidisciplinary trauma performance improvement committee (PI) and a trauma operations committee (ops).  However, a common question is, “How often do my committees need to meet?” Let’s start with your PI committee.

The answer, of course, is “it depends.” There is no cookie-cutter, one-size-fits-all answer. In this post, I’ll review the six factors you must consider when designing your meeting schedule.

Total Patient Volume

The number of patients seen at your center directly impacts your PI committee meeting schedule. The more patient encounters, the more likely that performance issues will arise and the more likely that some will need to be aired at the full committee meeting.

PI Issue Volume

What is the total number of PI items that your program identifies over time? Busy Level I centers may find five or ten items
every day!

In contrast, an average Level IV center may only find a PI issue to pursue every few weeks. This has a noticeable impact on how often these items need to be escalated, analyzed, and discussed at your PI meeting.

PI Issue Severity

What fraction of your PI cases actually require discussion by the full committee? How many can be processed and closed by the Trauma Program Manager alone (primary review) or with the Trauma Medical Director (secondary review)? Only complex cases that require the input of multiple liaisons actually need to go to the committee.

Alternate review pathways

There are more options for review other than the primary and secondary pathways mentioned in the previous paragraph. Typical options would be direct correspondence with a liaison for simple one-service issues or discussion (and good documentation) from a morbidity and mortality conference. The use of these alternatives will reduce the number of potential cases for your PI committee and decrease the overall number of meetings needed.

Age of your Trauma Program

Are you part of a mature, long-standing trauma center? Or is your program newly minted by the American College of Surgeons or state designating agency? Newer centers benefit from sending more items to the PI committee to build engagement of the liaisons and other attendees. More frequent meetings help get them used to the review process and the frank but friendly discussions required for effective PI review.

PI Committee “Leftovers”

How often do you need to table issues or cases until the next meeting because you ran out of time? If you are chronically short of time to discuss all the agenda items, it’s time to either make the meeting longer (groan!) or schedule them more frequently.

Bottom line: These six factors listed above must be considered when choosing your meeting schedule. Here are my starting suggestions for the ideal frequencies for adult trauma centers:

  • Level I – monthly (but high volume centers may need biweekly)
  • Moderate to high volume Level II – monthly
  • Lower volume Level II – bimonthly
  • Level III – bimonthly to quarterly
  • Level IV – quarterly

Most pediatric centers admit lower volumes and less complex patients, which usually only warrants a bimonthly meeting.
Remember, these are starting meeting frequencies only.
If you are a new trauma center, consider more frequent meetings for your first year to get your attendees used to and invested in the process. And if you need more cases to fill the meeting or have more hold-overs until the next meeting, adjust your calendar appropriately.

In my next post, I’ll cover this same topic for your trauma operations committee.

How Good Is The Erector Spinae Plane Block?

In my last post, I shared a video outlining the technique for providing an erector spinae plane block (ESPB). Today, I’ll review the most recent analysis of this procedure’s efficacy and safety.

As outlined previously, the ESPB targets the plane between the fascial layers of the thorax, providing analgesia in patients with rib fractures. The technique for use in trauma is relatively new, was first described in 2016, and studies on its effectiveness are finally beginning to accumulate. The most recent and comprehensive was recently published in the Clinical Journal of Pain by a group from Taiwan.

The authors performed a comprehensive search of papers published through 2025. They included only prospective studies comparing pain relief from fascial plane blocks (both ESPB and serratus anterior plane block (SAPB))  with epidural analgesia or no block. They identified only nine papers that included 600 patients, but only 5 used ESPB.

Here are the factoids:

  • Overall, fascial plane blocks in general (both SAPB and ESPB) significantly improved subjective pain scores during the first six hours, but were not after that for patients not receiving an epidural
  • When looking at SAPB alone, pain scores were improved during the first 24 hours; with ESPB alone, they were only improved during the first 6 hours.
  • Both types of plane blocks achieved pain scores similar to epidural analgesia
  • Both blocks decreased in-hospital opioid use, but this was not statistically significant
  • Hypotension occurred significantly less with fascial plane blocks compared to epidural analgesia
  • There was no difference in hospital length of stay with plane blocks compared to standard treatment

Bottom line: What does it all mean? First, there is still too little data to distinguish nuances in outcomes when comparing ESPBs and SAPBs. However, it appears that plane blocks result in less hypotension and so are a bit safer. However, subjective pain scores are only improved during the first 6 hours with ESPB. This suggests that there may be a significant placebo effect for this invasive procedure. Opioid use is the same.

With the exception of the first six hours, ESPB doesn’t look that exciting. It requires special equipment (ultrasound) and a trained provider to perform. It works as well as an epidural, which makes it more useful in patients with contraindications to this modality.

My take is that this may be a promising technique, but it’s still a bit too early to tell. This “large” series included only 600 patients, and fewer than half had the ESPB. So keep studying this procedure to see if it makes sense in the future.

Reference:  Efficacy and Safety of Serratus Anterior Plane Block and Erector Spinae Plane Block for Rib Fracture Pain: A Systematic Review and Meta-analysis. The Clinical Journal of Pain 42(2):e1334, February 2026. | DOI: 10.1097/AJP.0000000000001334